- High-flow nasal cannula (HFNC), at least 15 Lpm, on all patients undergoing intubation or who might need intubation.
- PEEP valve on every BVM.
- No longboards for ANY patient. Continue to use spinal precautions as appropriate, but that doesn't mean you need a long spinal board.
- Ketamine, followed by ketamine, rounded out by MORE KETAMINE for RSI induction.
- No Versed (midazolam) for intubation or post-intubation.
- No interruptions in compressions for any reason. Your survival decreases by 7% for every five seconds without compressions. We should be working on improved CPR and "see-through CPR" monitor technology, and don't you dare hold compressions while the monitor is charging!
- Tranexamic acid (TXA) for all hemodynamically unstable trauma patients.
- Let the fentanyl flow for intubations, especially after intubation. Pre-intubation benefits in head trauma.
- More intranasal medications.
- Use D25 instead of D50 when available.
- Treat septic nursing home patients like the real emergencies they are. IV fluids with 30-40 cc/kg bolus. IV access at a minimum to speed up the time to first antibiotics.
- Agitated/emotionally-disturbed patients should be recognized as real emergencies as well. These may be excited delirium. Treat with ketamine IM; doses as high as 4 mg/kg IM shown to be safe.
- No etomidate for sepsis or hypotensive patients.
- Push dose epinephrine for peri-intubation hypotension.
- Rotate people doing compressions at least every 3 minutes.
- Stop using BVMs on patients if RR is at least 4 or SPO2 is at least 94%. Instead, use high-flow nasal cannula with a nonrebreather on top.
- Every BLS should have a pulse oximeter. They are very affordable these days.
- Use a metronome for every cardiac arrest! If your monitor doesn't have one, download an app.
- No more nitroglycerin paste.
- Starting dosage of Zofran (ondansetron) for adults should be 8 mg.
Friday, January 2, 2015
Things We Can Do Better in 2015!
Here's my list of the top 20 things we can do better in 2015 based on what we learned in 2014 (or even before).

Thursday, January 1, 2015
Journal Club - January 5, 2015
- What: Weekly Journal Club
- Where: MONOC Education Building, 1415 Wyckoff Road, Ground Floor, Wall Township, NJ
- When: Monday, January 5, 2015 at 10:00 am
- Traumatic intra-abdominal hemorrhage control: Has current technology tipped the balance toward a role for prehospital intervention? http://www.ncbi.nlm.nih.gov/pubmed/25539217. Do we have the ability to control intra-abdominal hemorrhage in the prehospital environment? Does it matter with the new use of TXA?
- Apneic Oxygenation Was Associated With Decreased Desaturation Rates During Rapid Sequence Intubation by an Australian Helicopter Emergency Medicine Service. http://www.ncbi.nlm.nih.gov/pubmed/25536868. More evidence that this should be done on every patient needing intubation.
- EMS Patients and Walk-In Patients Presenting With Severe Sepsis: Differences in Management and Outcome. http://www.ncbi.nlm.nih.gov/pubmed/25502152. We reviewed an article earlier this year showing improved outcomes in septic patients when brought by ambulance. Does this study show the same thing? Come to journal club and find out!
- AWARE - AWAreness during REsuscitation - A prospective study. http://www.ncbi.nlm.nih.gov/pubmed/25301715. As we improve our high-quality CPR, we are hearing more anecdotal reports of patients having consciousness during compressions. Is this real life?!
Live-tweeting of the journal club @CCareAnywhere. #EMSJC
Sunday, December 28, 2014
2015: The Death of Longboards (Hopefully)
Myths in medicine take too long to go away. Longboards are yet another modality that
serve no purpose except to harm our patients.
Luckily this unnecessary tool used by EMS is going away around the
world. Many states and cities have
completely stopped using longboards for ALL patients. These places include areas within
Connecticut, Los Angeles, Kansas, Oregon, Missouri, Houston, New Mexico,.etc. No matter what your injuries are, in many
regions throughout the world, you will not be placed on a longboard, because they
are not being used at all.
These devices have hurt our patients since they offer no
benefit, yet we continue to use them in our region. The misconceptions about these devices are
enormous, yet the science tells us the following...
Longboards:
Longboards:
1.
Worsen the pain of patients resulting in more
unnecessary imaging tests and more radiation exposure.
2.
Cause respiratory compromise/decreased pulmonary
function by lying patients flat.
3.
Delay on-scene time for trauma patients.
4.
Result in pressure sores for patients by rapid tissue
breakdown from the board.
5.
Increase the risk of aspiration.
Unfortunately, we continue to have folks who spread misconceptions
about these devices, which prevent us from moving forward with evidence based
medicine. Luckily, a lot of places are
ignoring these folks and moving forward.
Some of the incorrect EMS statement that we have heard are:
1.
The DOT makes me put everyone on a longboard.
2.
I will get my license/certification taken away
if I don’t use a longboard.
3.
The DHSS does not allow patients to be brought
to hospitals without a longboard.
4.
If someone else puts a patient on a longboard, I
cannot take the patient off.
5.
It splints the back. (No, in fact it was only designed to help
extricate patients.)
6.
I will get sued if I don’t put someone on a
longboard
These are all ridiculous, and it is great that many places
around the country are moving forward with the science. Lets make 2015 the year we get rid of these
terrible devices in New Jersey and around the country.
Following the science, in January 2015, we will be telling
EMS providers that they do not need to place anyone on a longboard that is
brought into our hospital. Please join
us in getting rid of this outdated modality and provide the same information to
EMS.
References:
1. Chan D, Goldberg R, Tascne A, et al. The effect of spinal
immobilization on healthy volunteers. Ann Emerg Med. 1994;23:48-51.
2. March JA, Augband SC, Brown LH. Changes In Physical
Examination Caused By Use Of Spinal Immobilation. Prehospital Emerg Care. 2002;
6: 421-424.
3. Schriger DL, Larmon B, LeGarrick T, et al. Spinal
immobilization on a flat backboard: Does it result in neutral position of the cervical
spine? Am J Emerg Med. 1991;20:878-81.
4. Schafermeyer RW, Ribbeck BM, Gaskins J, et al.
Respiratory effects of spinal immobilization in children. Ann Emerg Med. 1991;20:1017-1019.
5. Bauer D, Kowalski R. Effect of spinal immobilization
devices on pulmonary function in the healthy nonsmoking man. Ann Emerg
Med.-1988; 17:915-8.
6. Barney RN, Cordell WH, Miller E. Pain associated with
immobilization on rigid spine boards (Abstract). Ann Emerg Med.1989; 18:918.
7. Chan D, Goldberg, RM, Jennifer Mason, J et al., Backboard Versus
Mattress Splint: A Comparison Of
Symptoms. The Journal of Emergency Medicine. 1996. 14:193-298.
8. Totten VY, Sugarman DB, Respiratory Effects Of Spinal Immobilization.
Prehosp Emerg Care 1999;3:347-352
9. Hauswald M, McNally T. Confusing Extrication with Immobilization:
The Inappropriate Use of Hard Spine Boards for Interhospital Transfers. Air Med
J. 2000; 19: 126-127
10. Hauswald M,Braude D.Spinal immobilization in trauma
patients: is it really necessary?_Current
Opinion in Critical Care 2002;8:566–70.
11. Hauswald M,Ong G,Tandberg D,Omar Z. Out-of-hospital spinal
immobilization: its effect on neurologic
injury. Academic Emergency Medicine 1998;5:214-219.
12. S. Abram S, Bulstrode C. Routine spinal
immobilization in trauma patients: What are the advantages and disadvantages? The
Surgeon. 2010;8:218–222.
13. Connell RA, Graham CA, Munro PT. Is spinal
immobilization necessary for all patients sustaining isolated penetrating
trauma? Injury. 2003;34: 912–914.
14. Kaups KL, Davis JW. Patients With Gunshot Wounds To The
Head Do Not Require Cervical Spine Immobilization And Evaluation. J Trauma.
1998; 44:865– 867.
15. Haut ER, Efron
DT, Adil H, Haider AH et al. Spine
Immobilization in Penetrating Trauma: More Harm Than Good? The Journal of
Trauma. 2010; 68.
16. Cornwell EE, Chang DC, Bonar JP, et al. Thoracolumbar
immobilization for trauma patients with torso gunshot wounds: is it necessary?
Arch Surg. 2001;136:324 –327.
17. Hauswald M, Ong G, Tandberg D, Omar Z. Out-of-hospital
spinal immobilization: its effect on neurologic injury. Acad Emerg Med. 1998;5:214
–219.
18. Kaups KL, Davis JW. Patients with gunshot wounds to the
head do not require cervical spine immobilization and evaluation. J Trauma.
1998;44:865–867.
19. Mark Hauswald, MD, Darren Braude, MD, MPH .Diffusion of
Medical Progress: Early Spinal Immobilization in the Emergency Department. Academic
Emergency Medicine 2007; 14:1087–1089.
Saturday, December 27, 2014
Journal Club - December 29, 2014
- What: Weekly Journal Club
- Where: MONOC Education Building, 1415 Wyckoff Road, Ground Floor, Wall Township, NJ
- When: Monday, December 29, 2014 at 10:00 am
- Tranexamic acid for traumatic brain injury: a systematic review and meta-analysis. http://www.ncbi.nlm.nih.gov/pubmed/25447601. Proof that we should get rid of the relative contraindication for isolated head trauma?
- Use of High-Flow Nasal Cannula Oxygen Therapy to Prevent Desaturation During Tracheal Intubation of Intensive Care Patients with Mild-to-Moderate Hypoxemia. http://www.ncbi.nlm.nih.gov/pubmed/25479117. If you're not putting a high-flow nasal cannula on every critically ill patient, you're doing something wrong! NO DESAT.
Live-tweeting of the journal club @CCareAnywhere.
End-Tidal Carbon Dioxide Monitoring in the Resuscitation of Critically Ill & Injured
Case:
73 yo
male with PMH of CAD s/p CABG, hypertension, other medical history unavailable.
C/C sudden cardiac witnessed by his wife at approximately 10:55 am. CPR
instructions given to his wife over the phone by the 911 operator. Police
arrived minutes later to continue CPR with an AED. The BLS team arrived shortly
after and assisted with the resuscitation using an AED, BVM, OPA and supplemental
oxygen. ALS arrived 14 minutes after the 911; BLS reported 3 AED
defibrillations prior to ALS arrival.
Initial
ECG is coarse ventricular fibrillation and the patient was defibrillated at
360J by ALS. High-Quality CPR continued. Vascular access established with a right proximal humoral IO,
1mg of epinephrine given and repeated every 4 minutes during CPR. Paramedics
intubated the patient without an interruption in chest compressions; initial
EtCO2 is 40 mmHg. 2 minutes later, the patient is noted to be in
refractory VFIB despite serial defibrillations and anti-dysrhythmics. A total
of 14 defibrillations, amiodarone, magnesium and lidocaine were required to
convert the VFIB to an organized pulseless sinus ECG rhythm with a QRS width of
160 msec. The patient also received calcium and sodium bicarbonate. Return of
spontaneous circulation (ROSC) was noted 38 minutes into the resuscitation.
This patient received approximately 1200 cc of crystalloid IVF, atropine and
push dose pressors (1:100k Epi) to maintain hemodynamics during transfer to the
ED. Pulses were lost during
transport for 8 minutes and required CPR and additional epinephrine. Below is a
plot of his EtCO2 and respiratory rate versus time. ROSC#1 @ t=38 minutes and ROSC#2 at t=65 minutes.
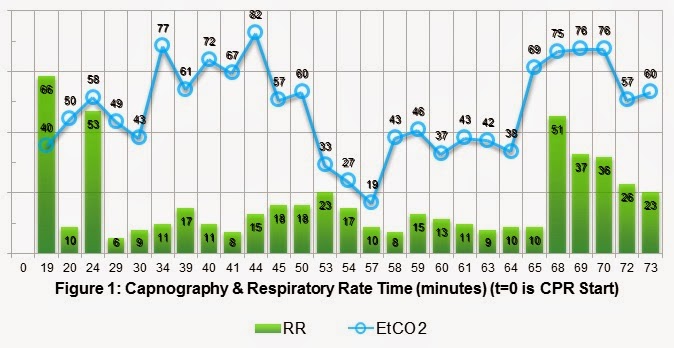
Kodali and
colleagues recently published an excellent review of the usefulness of
capnography in Care of the Critically Ill and Injured. The literature search
was quite extensive looking at peer review papers from 1960 to 2014, covering
primary research, case reports and other review papers. Figure 2 is a summary
of the different clinical applications. Conformation of endotracheal intubation
is quoted in Kodali's paper as both 100% sensitive and specific, with 3 decades
of data for detecting correct tube placement. This has been known for a while
in EM and nice to repeat as often as possible because few tests have that level
of certainty. Waveform Capnography is the most definitive evidence of
correct endotracheal tube placement, thus eradicating the unrecognized
esophageal intubation.

Capnography
has been demonstrated to reflect the patient’s cardiac output (CO) during a
resuscitation based on the height of the waveform. The greater the CO the more
CO2 is off loaded in the lungs and measured on exhalation. Current Evidence demonstrate EtCO2 levels less than 10 mmHg
during chest compression is not likely to generate ROSC, so every effort should
be made to maximize the quality of CPR and treat reversible causes of arrest.
A certain
level of prognostication or prediction is also gained by the routine use of
capnography during CPR. Abrupt increases in EtCO2, generally a jump greater than 10-20 mmHg, is a marker of
ROSC, and, conversely, refractory EtCO2 values less than 10 mmHg has
identified 100% of patients who were unsuccessfully resuscitated. Kodali
found that the cumulative max EtCO2 > 20 mmHg at all time points
measured between 5 and 10 minutes post-intubation best predicted ROSC
(sensitivity of 88%, specificity 77%). EtCO2 is a valuable
tool in real-time decision-making during resuscitation.
Other
uses of capnography include monitoring of airway patency and respiratory rates.
The waveform capnograph and the ability to set warning alarms will instantly
alert providers to apneic conditions, such as obstruction or displacement. In
clinical situations where a patient is sedated or obtunded, EtCO2
will herald hypoventilation or apnea much sooner than traditional SpO2
monitoring.
Back to
our case, after reviewing figure #1, we can apply all the previously mentioned
key points to capnography. EtCO2 definitively confirmed ETT
placement. ROSC was predicted at t=10 minutes by an EtCO2 value
greater than 20 mmHg. High-Quality CPR was performed while reversible causes of
the arrest were managed. ETT patency was maintained throughout the encounter
and transfer to the ED. This would have been a great case to use 720 J Double
Sequential Defibrillation (DSD) for refractory ventricular fibrillation.
References:
1.
Goto,
Y; etal. “Termination-of-resuscitation rule for
emergency department physicians treating out-of-hospital cardiac arrest
patients: an observational cohort study”. Critical Care.
2013;17:R235.
2.
Kodali,
BS; etal. “Capnography during cardiopulmonary
resuscitation: Current evidence and future directions”.
J Emerg Trauma Shock. 2014;7(4):332-340.
3.
Meaney, PA; etal. “Cardiopulmonary
Resuscitation Quality: Improving Cardiac
Resuscitation Outcomes Both Inside and
Outside the Hospital. A Consensus Statement From the American Heart Association
Endorsed by the American College of Emergency Physicians and the Society of
Critical Care Medicine”. Circulation.
2013;128:417-435.
4.
Neumar, RW; etal. “Part 8: Adult Advanced
Cardiovascular Life Support: 2010 American Heart Association Guidelines for
Cardiopulmonary Resuscitation and Emergency Cardiovascular Care”. Circulation.
2010;122[suppl 3]:S729–S767.
Tuesday, December 16, 2014
Hydrofluoric Acid Burns
A 32 year old gentleman was welding
stainless steel and sustained a 75% concentration hydrofluoric acid burn to the
right hand. Upon initial assessment,
vital signs are unremarkable with a RR-12 @ 99% RA and BP 128/86. On physical exam there are no visible signs
of damage to the right hand and he seems to be neurovascularly intact. Upon auscultation of the heart and lungs,
diffuse expiratory wheezing is noted. A
12 lead EKG is obtained and pictured below.
What are your initial management options and continuing concerns throughout
treatment of this patient?

Hydrogen fluoride and its aqueous form, hydrofluoric acid,
are utilized in many manufacturing processes.
Uses include: cleaning products, oil refining, Teflon production,
aluminum production, and etching of carbon and stainless steels as well as
ceramics. Exposures most commonly seen
involve explosions of Teflon containing compounds, deployment of automated fire
suppression systems, and exposure to cleaning solutions.
The high lipid solubility of HF allows it to penetrate
tissues rapidly. Immediate exposure may
result in a painless burn, as the substance interferes with nervous system
function. This could delay contact of
emergency services and also mask the severity of exposures. Extreme pain ensues
as the chemical begins to interact with ions in the tissues. The fluoride ion in the compound has a high
electronegativity. This quality imparts
a high affinity for positively charged ions in the body, allowing HF to readily
interact with calcium and magnesium in the body. The combination of hypocalcemia and
hypomagnesemia promotes prolongation of the QT interval, ventricular
arrhythmias, tetany, and seizures. HF
burns involving greater than 2% body surface area or HF with a
concentration of greater than 20% have the highest likelihood of causing
systemic toxicity and fatal arrhythmia.
As with most chemical exposures, copious irrigation is
encouraged. In addition to irrigation,
literature has shown improved immediate pain relief and long-term
outcomes with application of topical 2.5% calcium gluconate. If calcium gel is not readily available, it can be made by mixing 3.5 g of calcium gluconate powder with approximately 5 ounces
of water soluble surgical lubricant. For
continued pain after topical application, 5% calcium gluconate subcutaneous injections
may be utilized for local infiltration.
The appropriate dose is 0.5 mL per cm² burn area. Local
infiltration is not recommended for digits. Up to 40 mL of 10% calcium
gluconate can be given intra-arterially or intravenously with an inflated blood
pressure cuff to localize the treatment if infiltration is not effective or not an option.
In
the case presented, cardiac monitoring and topical calcium application are the
most important management factors in the pre-hospital setting. A seemingly mild case of an HF burn to the
hand could decompensate quickly due to cardiac dysrhythmia. Keep in mind that 2% BSA can include a burn
only involving the hand! In a
hospital setting, continuous cardiac and electrolyte monitoring guide management. Calcium can be administered intravenously in a 1000 mg dose infused over 2 minutes. Magnesium replacement of 4g IV given over 20
minutes is also recommended.
References
1. Nathanson
L A, McClennen S, Safran C, Goldberger AL. ECG Wave-Maven: Self-Assessment
Program for Students and Clinicians. http://ecg.bidmc.harvard.edu. Accessed 16
December 2014.
2. Höjer J, Personne M, Hultén P, Ludwigs U. Topical treatments for
hydrofluoric acid burns: a blind controlled experimental study. J Toxicol Clin
Toxicol. 2002;40(7):861-866. http://www.ncbi.nlm.nih.gov/pubmed/12507055.
3. Lewis
N, Lewand M, Howland N, Hoffman R, Goldfrank L, Flommenbaum L; Goldfrank’s Toxicologic Emergencies, Ninth
Edition; 9th ed; 2010. 787-803.
4. Wu
M-L, Yang C-C, Ger J, Tsai W-J, Deng J-F. Acute hydrofluoric acid exposure
reported to Taiwan Poison Control Center, 1991-2010. Hum Exp Toxicol.
2014;33(5):449-454. doi:10.1177/0960327113499165.
Tuesday, December 9, 2014
Journal Club - December 15, 2014
- What: Weekly Journal Club
- Where: Newark Beth Israel Medical Center, D-11, 201 Lyons Avenue, Newark, NJ
- When: December 15, 2014 at 2:00 pm (note the later time!)
We have an exciting lineup of articles this week! Come join us to discuss them.
- Tranexamic acid administration to pediatric trauma patients in a combat setting: The pediatric trauma and tranexamic acid study (PED-TRAX). http://www.ncbi.nlm.nih.gov/pubmed/?term=PED-TRAX. Forget the 16 year-old age cutoff for TXA! Big implications for pre-hospital and trauma care.
- A randomized controlled trial of oxygen therapy in acute myocardial infarction Air Verses [sic] Oxygen In myocarDial infarction Study (AVOID Study). http://www.medscape.com/viewarticle/835297_print and http://www.ncbi.nlm.nih.gov/pubmed/22424003. "MONA" takes another hit? Join us Monday to find out!
- Outcomes After Out-of-Hospital Cardiac Arrest Treated by Basic vs Advanced Life Support. http://www.ncbi.nlm.nih.gov/pubmed/25419698. The much-discussed study about BLS vs ALS for OHCA. Does this surprise any of us following the literature?
Live-tweeting of the journal club @CCareAnywhere.
Subscribe to:
Posts (Atom)